
Forced Normalization with Intractable Seizures: Latest Research and Recommendations
A deep exploration of the interplay between seizure control and psychiatric disturbances
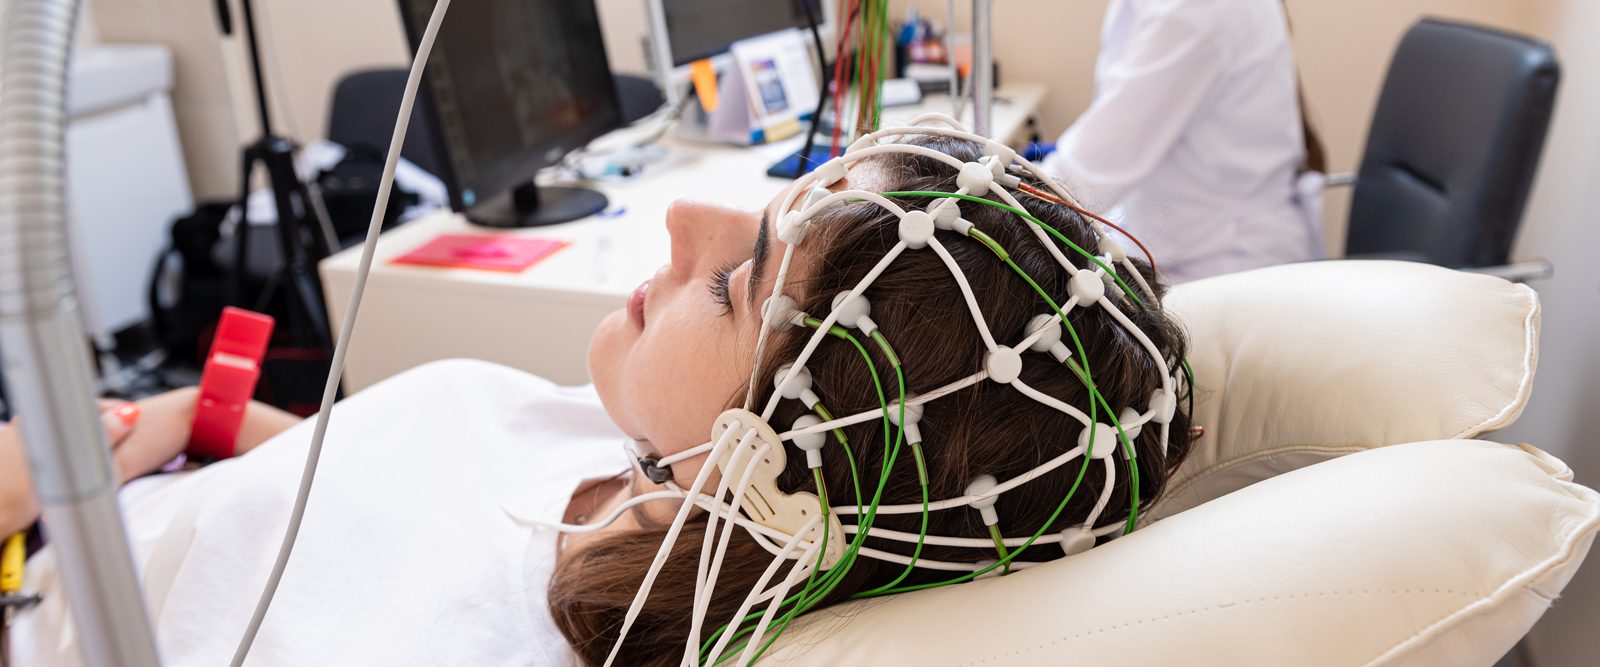
Key Highlights
- Emergence of Psychiatric Symptoms: Research reveals a complex phenomenon where seizure control coincides with unexpected psychiatric symptoms.
- Medication Impact: Modern antiseizure medications, including novel agents like cenobamate, are linked with forced normalization events in some patients.
- Multidisciplinary Management: Early detection, careful monitoring, and coordinated treatment between neurology and psychiatry are critical for optimal outcomes.
Overview and Clinical Characteristics
Forced normalization is a phenomenon that has attracted significant research interest in recent years, particularly in relation to its occurrence in patients with intractable seizures. The condition occurs when effective seizure control, whether through pharmacological intervention, surgery, or other therapeutic modalities, paradoxically gives rise to psychiatric disturbances. These disturbances may range from psychosis and mood disorders to severe behavioral changes. In clinical settings, forced normalization serves as a cautionary indicator that achieving seizure control does not necessarily equate to overall clinical stability.
Historically, forced normalization was first described in the mid-20th century by Heinrich Landolt as a scenario in which the electroencephalogram (EEG) normalizes in association with the onset of psychiatric symptoms. Recent research has further detailed the temporal window of symptom emergence; typically, psychiatric disturbances develop within 30 days after significant alterations in antiepileptic drug (AED) therapy. Although the underlying pathophysiological mechanisms remain only partly understood, current studies suggest a complex interplay between the neurobiology of epilepsy and psychiatric conditions.
Pathophysiology and Underlying Mechanisms
Neurotransmitter and Electrophysiological Dynamics
The neurobiological underpinnings of forced normalization revolve around changes in neurotransmitter dynamics and cortical excitability. As epileptiform discharges diminish due to effective antiseizure medications, alterations in the balance between excitatory and inhibitory signaling may unmask or trigger psychiatric symptoms.
Research suggests that the normalization of the EEG, while beneficial in reducing the frequency of seizures, may simultaneously induce neurotransmitter dysregulation. For instance, the reduction in excessive excitatory neurotransmission might alter dopaminergic and serotonergic pathways, contributing to psychotic and mood symptoms. Some studies have indicated that an overcorrection in neuronal activity, where the brain’s regulatory systems overshoot the therapeutic target, can lead to an imbalance that affects behavior and cognition.
The association of certain medications with forced normalization further supports the theory that drug-induced changes in neurotransmitter activity are implicated. Drugs such as zonisamide, levetiracetam, and the newer agent cenobamate have been specifically linked with the emergence of psychiatric symptoms in controlled patients. These findings underscore that while seizure suppression is achieved, the accompanying side effects of modulating brain excitability might predispose patients to developing neuropsychiatric complications.
Diagnostic Criteria and Challenges
Diagnosis of forced normalization is complex due to the overlapping symptoms with primary psychiatric disorders. Clinicians consider the following criteria in establishing diagnosis:
- Temporal Onset: Psychiatric symptoms typically appear within a short period (less than 30 days) following a substantial reduction or complete cessation of seizures.
- EEG Correlation: There is often normalization or significant improvement in the EEG readings concurrent with the psychiatric episode.
- Exclusion of Alternative Causes: A thorough examination is conducted to rule out other conditions, including a primary psychiatric disorder or effects induced by other medications.
Despite these guidelines, variability in patient presentations makes the differential diagnosis challenging. Some patients may manifest mild behavioral changes, while others develop severe psychotic episodes. The heterogeneity of clinical presentations further complicates the diagnostic process, meaning that awareness and vigilance among healthcare providers are essential for timely intervention.
Impact of Antiseizure Medications
Drug-Induced Changes and Case Studies
The relationship between antiseizure medications (ASMs) and forced normalization has been a focal point of contemporary research. Numerous studies have reported that while many ASMs effectively reduce seizure frequency, they may, in certain susceptible individuals, trigger psychiatric symptoms. This paradoxical effect is particularly recognized with medications such as:
- Zonisamide – Frequently used in epilepsy control but associated with neuropsychiatric side effects in some cases.
- Levetiracetam – Has a well-documented profile of behavioral disturbances that may lead to forced normalization phenomena.
- Cenobamate – Recent case reports have highlighted its potential role in the emergence of forced normalization, with some patients developing severe psychiatric symptoms after achieving good seizure control.
Case studies, including systematic reviews, underline that while these medications are effective in controlling seizures, their psychiatric side effects necessitate careful dose management and patient monitoring. In some instances, modifying the ASM regimen or supplementing treatment with targeted antipsychotic medications has yielded positive results in mitigating the psychiatric manifestations without compromising seizure control.
Therapeutic Adjustments and Considerations
Given the potential for forced normalization, treatment strategies require a balanced approach. The therapeutic options include:
- Adjusting Medication Dosages: In patients displaying early signs of psychiatric disturbances, clinicians might reduce the dosage of the implicated ASM while maintaining seizure control.
- Switching Medications: In some cases, transitioning to another ASM with a lower propensity for psychiatric side effects has been successful.
- Psychiatric Medications: The introduction of antipsychotic or mood-stabilizing drugs is often necessary to counteract the behavioral symptoms. Such interventions should be carefully integrated with ongoing epilepsy management.
- Alternative Treatments: Emerging therapies, including electroconvulsive therapy (ECT), have been explored for patients with refractory forced normalization symptoms. Although not first-line, ECT represents an adjunct therapy when conventional methods are insufficient.
The consensus among recent research indicates that a multifaceted treatment plan is essential. Management should involve personalized strategies assessed on a case-by-case basis, with continuous cross-disciplinary collaboration between neurologists and psychiatrists.
Multidisciplinary Approach and Future Directions
Coordination of Neurology and Psychiatry
A consistent theme in the literature is the importance of a multidisciplinary approach in managing forced normalization. Because the phenomenon straddles the domains of neurology and psychiatry, effective management depends on a coordinated, team-based approach. Joint consultations and regular communication between specialties enable more precise adjustment of therapies and prompt recognition of adverse effects.
As part of clinical practice, patient monitoring protocols now often include regular EEG assessments along with psychiatric evaluations. These collaborative protocols help in early detection and timely modification of treatment plans, ultimately improving patient outcomes and minimizing the disruptive impact of psychiatric symptoms.
Research Gaps and Emerging Innovations
Despite significant advancements, several research gaps remain. The precise pathophysiology of forced normalization is not fully delineated, and ongoing studies continue to investigate:
- Genetic and Molecular Factors: Exploration of genetic markers that may predispose patients to forced normalization is an area of considerable interest. Understanding these factors could eventually facilitate personalized treatment strategies.
- Long-term Outcomes: There is a critical need for longitudinal studies to evaluate the long-term psychiatric and neurological outcomes in patients diagnosed with forced normalization.
- Innovative Therapeutic Modalities: The potential of novel treatments such as neurostimulation and advanced pharmacotherapy represents promising avenues. Research into adaptive therapies that dynamically adjust ASM dosages based on real-time EEG and behavioral feedback could radically improve quality of life for patients.
Future research is expected to further elucidate the dynamic interplay between seizure control and psychiatric health, leading to more refined diagnostic criteria and therapeutic algorithms. This will ultimately result in individualized, evidence-based treatment plans that balance both seizure suppression and mental health stabilization.
Integrated Clinical Data
Summary Table of Key Aspects
| Aspect | Details |
|---|---|
| Definition | Emergence of psychiatric symptoms (e.g., psychosis, mood disorders) following seizure reduction or normalization of EEG readings. |
| Associated Medications | Antiseizure medications such as zonisamide, levetiracetam, and cenobamate; possible role of other interventions like vagus nerve stimulation. |
| Diagnostic Criteria | Rapid onset of psychiatric symptoms within 30 days of therapeutic change, simultaneous seizure control, and EEG normalization; exclusion of other psychiatric conditions. |
| Treatment Approaches | Medication adjustments, potential addition of antipsychotics, multidisciplinary care; alternative therapies including ECT when conventional treatments are ineffective. |
| Future Research Areas | Clarification of neurobiological mechanisms, genetic predispositions, long-term clinical outcomes, and development of smarter therapeutic protocols. |
Clinical Recommendations and Patient Management
Early Detection and Monitoring
Recognizing early signs of forced normalization is critical for mitigating its impact on quality of life. Clinicians are advised to implement comprehensive monitoring protocols, which include:
- Regular EEG Assessments: Monitoring for normalization of EEG activity serves as an indicator of potential forced normalization, even in the absence of overt behavioral changes.
- Psychiatric Evaluations: Close collaboration with mental health professionals ensures that subtle psychiatric symptoms are identified and managed in a timely manner.
- Frequent Clinical Visits: For patients undergoing significant changes in their antiseizure medication regimen, more frequent clinical follow-ups help catch early psychiatric anomalies before they escalate.
Early intervention is essential. A rapid response can allow for modifications in the treatment plan to either reduce the dosage of the implicated medication or introduce psychiatric supportive therapies, thereby balancing seizure control with mental stability.
Balancing Seizure Control with Psychiatric Health
Achieving an optimal balance between seizure suppression and psychiatric stability is the central challenge in managing forced normalization. Clinicians must carefully weigh the benefits of seizure control against the risk of inducing psychiatric disturbances. Some key strategies include:
- Customized Medication Plans: Tailor the antiepileptic regimen based on the patient’s seizure history, psychiatric vulnerability, and drug response profile.
- Multidisciplinary Team Meetings: Regular interdisciplinary meetings facilitate the exchange of insights between neurology, psychiatry, and pharmacology experts.
- Adjustment Protocols: Develop and implement clear protocols for tapering or substituting ASMs when psychiatric side effects are observed.
- Patient Education: Informing patients and caregivers about the risks and signs of forced normalization can promote early reporting and prompt intervention.
These recommendations, derived from a synthesis of recent clinical studies and case series, emphasize that while forced normalization presents considerable challenges, strategic management can mitigate risks without sacrificing therapeutic efficacy.
Translational Insights and Emerging Therapies
Innovative Treatment Modalities
Beyond traditional pharmacotherapy, emerging treatment modalities are currently under investigation for patients who exhibit forced normalization. One such promising approach is the use of neurostimulation techniques, which include:
- Electroconvulsive Therapy (ECT): Particularly for patients with refractory psychiatric symptoms, ECT has shown effectiveness in mitigating psychosis while preserving seizure control.
- Vagus Nerve Stimulation (VNS): Although primarily aimed at reducing seizure frequency, VNS can occasionally influence psychiatric symptoms. Its adjustment may help avoid the onset of forced normalization.
- Adaptive Neurostimulation: Research is ongoing into devices that continuously monitor EEG activity and adjust stimulation parameters in real time, potentially offering a more balanced approach to managing both seizures and psychiatric symptoms.
These advanced therapeutic strategies signal a future where interventions can be dynamically tuned to manage the dual challenges of epileptic control and psychiatric health, ultimately offering personalized treatment that adapts to patient-specific needs.
Guidelines for Clinical Practice
Based on the latest research, the following guidelines are recommended for clinicians:
- Incorporate routine neurological and psychiatric evaluations when modifying the antiepileptic regimen.
- Create individualized treatment protocols that include predefined markers for adjusting medications if forced normalization symptoms emerge.
- Foster proactive multidisciplinary collaboration to ensure coordinated adjustment of both seizure and behavioral management strategies.
- Ensure patient education and engagement in monitoring symptoms, thereby empowering patients to report early changes that could indicate forced normalization.
The emphasis on a collaborative, patient-centric approach has been validated by case series and systematic reviews, highlighting that successful management of forced normalization hinges on early detection, tailored treatment strategies, and interdisciplinary care.
References
- Forced Normalization: A Case Series - Seizure Journal
- Forced Normalization and Epilepsy - Frontiers in Integrative Neuroscience
-
Mechanisms of Forced Normalization - ScienceDirect
- Systematic Review on Forced Normalization - PubMed
-
Epilepsy and Psychiatric Disturbances - PMC
Recommended Related Queries
Last updated March 19, 2025