
Exploring Granulomatous Reactions to HA Fillers Mimicking Tumors
Delve into diagnostic challenges and management strategies when HA fillers present as salivary gland neoplasms
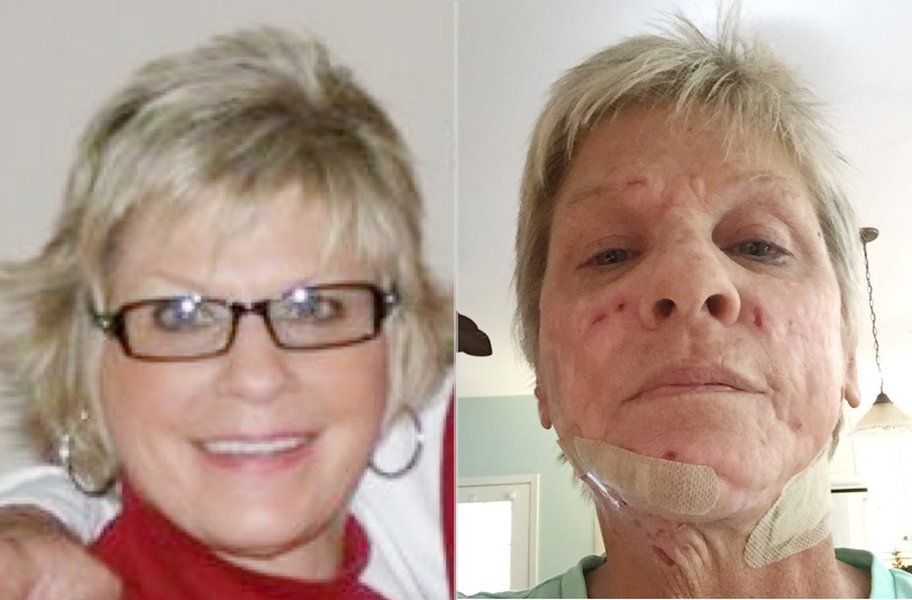
Key Highlights
- Diagnostic Challenge: Granulomatous reactions from HA fillers can mimic salivary gland tumors clinically, creating diagnostic complexity.
- Clinical Evaluation: Comprehensive evaluation using imaging, cytopathology, and clinical history is essential to differentiate benign inflammatory processes from neoplastic lesions.
- Treatment Options: Effective management includes conservative measures, intralesional corticosteroids, hyaluronidase treatment, and in some cases, surgical intervention.
Overview and Pathophysiology
Granulomatous reactions to hyaluronic acid (HA) dermal fillers represent a complex, immune-mediated response that can occur as a delayed adverse event. Although HA is a naturally occurring substance in the human body, its use in cosmetic filler procedures may, in rare instances, trigger a granulomatous reaction. This reaction is characterized by an inflammatory response with multinucleated giant cells and macrophages forming around the filler material.
In clinical practice, patients may present months to years after receiving HA injections with firm nodules, localized swelling, and peri-oral masses. These clinical manifestations can closely resemble salivary gland tumors such as pleomorphic adenoma or mucoepidermoid carcinoma. Such similarities pose a significant diagnostic challenge, necessitating a careful differential diagnosis to avoid misinterpretation as malignant lesions.
Clinical Presentation
Symptoms and Signs
Patients with a granulomatous reaction from HA fillers can present a variety of signs, including:
- Firm, palpable masses in the peri-oral region.
- Swelling and nodularity that may mimic tumor growth.
- Mild to moderate pain or tenderness in the affected area.
- Progression over time, with some cases emerging years following the initial injection.
- Adverse reactions that can resemble benign salivary gland tumors or mimic other neoplastic conditions.
These signs underscore the need for thorough clinical evaluation and a careful review of the patient's injection history.
Imaging and Biopsy
The differentiation between a granulomatous reaction and a salivary gland tumor is primarily achieved through diagnostic imaging and histopathological analysis. Key diagnostic tools include:
- Ultrasound, CT, and MRI: Imaging may reveal masses with characteristics similar to tumors. However, imaging alone is not definitive.
- Fine-needle Aspiration Cytology (FNAC): FNAC is a valuable tool for obtaining a tissue sample. Cytological analysis typically shows granulomatous inflammation without epithelial components that are typically seen in neoplastic tumors.
- Histopathologic Evaluation: A biopsy sample stained and analyzed under microscopy can confirm the granulomatous nature of the reaction, showing features such as multinucleated giant cells and inflammatory infiltrates around HA particles.
The clinical history – including the timeline since HA filler injection – is of paramount importance. Detailed patient history helps in correlating the onset of symptoms with the cosmetic procedure, thus guiding the diagnostic process.
Differential Diagnosis
Distinguishing Features
The clinical presentation of a granulomatous reaction to HA fillers overlaps with that of salivary gland tumors. However, there are distinguishing features:
- Absence of Neoplastic Cells: On biopsy, the lack of atypical epithelial cells largely rules out malignancy.
- Delayed Onset: Granulomatous reactions often manifest months to years after the injection, as opposed to the more rapid growth typically seen in neoplasms.
- Localized Reaction: While salivary gland tumors predominantly arise in glandular tissues, granulomatous reactions may occur at the site of injection and can be more diffuse.
These features are pivotal for clinicians to avoid unnecessary surgical interventions aimed at treating cancers.
Differential Considerations
In addition to salivary gland tumors, differential diagnoses include:
- Granulomatous infections (e.g., mycobacterial or fungal infections).
- Other soft-tissue neoplasms.
- Foreign body reactions triggered by other injected materials, such as silicone or bovine collagen-based fillers.
A systematic approach combining clinical history, imaging, and tissue analysis is paramount in distinguishing these conditions.
Pathophysiology and Mechanism
Understanding the Immune Response
The granulomatous reaction is primarily an immune-mediated process. The body recognizes the injected HA as a foreign substance despite its natural occurrence in the dermis. In some individuals, an aberrant immune response may develop, leading to:
- Activation of macrophages and subsequent fusion to form multinucleated giant cells.
- Recruitment of lymphocytes and other inflammatory cells to the site.
- Formation of granulomas, which are collections of inflammatory cells attempting to wall off and isolate the filler material.
The exact triggers that tip the immune balance toward a granulomatous reaction remain a subject of ongoing research. It appears that both the nature of the filler and individual patient immunological differences contribute to the reaction.
Illustrative Mindmap
The following diagram provides a visual representation of the key stages in the development of a granulomatous reaction to HA dermal fillers.
Diagnostic Evaluation and Management Strategies
Comprehensive Diagnostic Approach
Diagnosis of a granulomatous reaction that mimics salivary gland neoplasms requires a multifaceted examination approach. This approach includes:
- Detailed patient history review regarding previous cosmetic procedures, specifically the type of filler used and timing of injections.
- High-resolution imaging studies (ultrasound, CT, MRI) to precisely localize the mass and evaluate its characteristics.
- Fine-needle aspiration cytology (FNAC) and/or a core biopsy to obtain histopathological confirmation. The cytology often reveals granulomatous inflammation without the epithelial structures associated with salivary gland tumors.
- Laboratory tests to rule out infectious etiologies if the clinical context suggests an alternative diagnosis.
The integration of clinical, radiological, and pathological findings is critical to secure a correct diagnosis and to avoid misinterpretation as a malignant neoplasm.
Management and Treatment Modalities
Once a granulomatous reaction is confirmed, several treatment options are available based on severity:
| Treatment Option | Indication | Notes |
|---|---|---|
| Conservative Management | Mild reactions | Observation, NSAIDs, and corticosteroids may suffice. |
| Intralesional Corticosteroids | Moderate inflammation | Direct injection can reduce inflammation effectively. |
| Hyaluronidase Injection | High HA concentration | Dissolves hyaluronic acid filler and mitigates reaction. |
| Surgical Excision | Severe or refractory cases | Considered when conservative measures fail. |
In some cases, patients may benefit from a combination of treatments. For instance, removal of the HA filler through hyaluronidase injection combined with corticosteroids can provide significant symptomatic relief. The decision on management depends on the extent of the granulomatous reaction, patient symptoms, and aesthetic concerns.
Adjunctive Imaging and Cytopathology
Advanced imaging modalities are instrumental in delineating the lesion's boundaries and distinguishing granulomatous inflammation from neoplastic processes. Diagnostic imaging studies such as ultrasound and MRI offer insights into the lesion's internal architecture. Additionally, cytological assessment plays a crucial role. The absence of epithelial cells in granulomatous lesions contrasts sharply with the cellular profiles typically observed in salivary gland tumors.
Advanced Data Visualization
Radar Chart Analysis
The following radar chart provides a complex analysis of various factors involved in diagnosing and managing granulomatous reactions to HA fillers, compared to true neoplastic processes of the salivary glands. The datasets reflect multiple dimensions such as diagnostic clarity, treatment effectiveness, patient symptom severity, and the risk of misdiagnosis.
Educational Video Resource
Watch and Learn: Granulomatous Reactions Explained
To further enhance your understanding, the video below illustrates the clinical presentation and management of granulomatous reactions to dermal fillers. It explains the underlying pathophysiological mechanisms, diagnostic challenges, and treatment options:
The embedded video provides additional context and real-life case studies which underscore the importance of distinguishing these reactions from malignant neoplasms.
Frequently Asked Questions (FAQ)
What is a granulomatous reaction in the context of HA fillers?
A granulomatous reaction is an immune-mediated inflammatory response in which the body forms granulomas—clusters of activated macrophages and multinucleated giant cells—around the filler material. This reaction can produce firm nodules and mimic the clinical appearance of neoplastic growths such as salivary gland tumors.
How can clinicians differentiate between a granulomatous reaction and a salivary gland tumor?
Differentiation typically involves a combination of patient history, imaging studies (ultrasound, MRI, CT), and tissue sampling through fine-needle aspiration or biopsy. Histopathological examination is essential to identify granulomatous inflammation without the characteristic epithelial components seen in salivary gland tumors.
What treatment options exist for managing these reactions?
Treatment options are tailored based on severity. Conservative management may include observation and the use of NSAIDs or corticosteroids. In cases with significant granulomatous inflammation, intralesional corticosteroid injections, hyaluronidase injections to dissolve the filler, or even surgical excision may be recommended.
Why do these granulomatous reactions occur?
Although hyaluronic acid is a naturally occurring substance, its injection as a filler can elicit an immune response in some individuals. This reaction likely results from individual differences in immune sensitivity and the physical characteristics of the filler, which in some cases lead to the formation of granulomas.
References
-
Case Report on Delayed Adverse Reaction – NCBI
- Granulomatous Reaction and Parotid Mimicry – PubMed
- Oral Granulomatous Reaction Analysis – JOMS
- Filler Reaction and Buccal Tumor Mimicry – PubMed
-
Granulomatous Reaction Diagnosis by FNA – PMC
Recommended Related Queries
Last updated March 30, 2025