
Unlocking the Mystery: How Chronic Immobilization Impacts Your Body's Phosphorus Balance
Discover the intricate ways prolonged inactivity alters crucial mineral levels, particularly phosphorus.
When movement is restricted for extended periods, whether due to injury, illness, or other conditions requiring bed rest or limited mobility, the body undergoes various physiological changes. One significant alteration involves the metabolism of minerals essential for bone health and overall function, notably phosphorus. Understanding what happens to phosphorus levels during chronic immobilization is crucial for managing health during these periods.
Key Insights on Immobilization and Phosphorus
- Increased Serum Phosphorus: Chronic immobilization generally leads to higher levels of phosphorus in the bloodstream, a condition known as hyperphosphatemia.
- Bone Resorption is Key: The primary driver is accelerated bone breakdown (resorption) due to the lack of mechanical stress, releasing phosphorus stored in bones.
- Kidney Function Adapts: Changes in hormonal regulation, particularly involving Parathyroid Hormone (PTH), reduce the kidneys' ability to excrete excess phosphorus, further contributing to elevated levels.
The Mechanisms Behind Phosphorus Changes
The rise in phosphorus levels during chronic immobilization isn't random; it's a result of specific physiological adaptations and imbalances triggered by inactivity.
The Crucial Role of Bone Resorption
Why Bones Release Phosphorus
Bones serve as the body's main reservoir for both calcium and phosphorus, storing them primarily as hydroxyapatite crystals. Mechanical stress from activities like walking and weight-bearing exercises signals the body to maintain bone density. When this stress is absent during prolonged immobilization, the balance shifts.
Bone remodeling is a continuous process involving bone formation (by osteoblasts) and bone resorption (by osteoclasts). Inactivity significantly reduces the signals for bone formation while simultaneously enhancing bone resorption. This increased breakdown of bone tissue releases calcium and phosphorus into the bloodstream faster than they can be utilized or excreted, leading to elevated serum levels of both minerals.

Patient immobilization, often necessary after fractures or paralysis, triggers changes in bone metabolism.
Impact on Renal Phosphorus Handling
Hormonal Shifts and Kidney Function
Parathyroid Hormone (PTH) plays a vital role in regulating calcium and phosphorus. Typically, PTH helps lower blood phosphorus levels by promoting its excretion in the urine via the kidneys. However, studies indicate that chronic immobilization can lead to a downregulation or altered sensitivity to PTH.
This suppression of PTH activity means the kidneys become less effective at filtering out excess phosphorus. The renal threshold for phosphorus reabsorption increases, causing more phosphorus to be retained in the body instead of being excreted. This reduced urinary clearance exacerbates the hyperphosphatemia initiated by bone resorption. Some research notes a potential delay in the rise of serum phosphorus, suggesting these renal adaptations develop over time during sustained immobilization.
Clinical Implications and Observations
The changes in phosphorus levels during chronic immobilization are not just biochemical curiosities; they have tangible effects on health and are observed consistently in clinical settings.
Hyperphosphatemia and Associated Conditions
The resulting hyperphosphatemia can contribute to several health issues. Chronically elevated phosphorus is often seen alongside high-normal or elevated serum calcium levels (hypercalcemia), further disrupting mineral balance. This imbalance can increase the risk of:
- Osteoporosis: The underlying bone resorption weakens bones over time.
- Vascular Calcification: Excess phosphorus can bind with calcium and deposit in blood vessels and soft tissues, potentially increasing cardiovascular risk, especially if kidney function is also compromised.
- Crystalluria: Formation of crystals (like calcium phosphate) in the urine, which can sometimes lead to kidney stones.
Clinical studies have documented serum phosphorus levels ranging from mildly elevated (around 6.5 mg/dL) to significantly high (over 8.0 mg/dL) in immobilized individuals, particularly those with spinal cord injuries or prolonged bed rest after trauma.
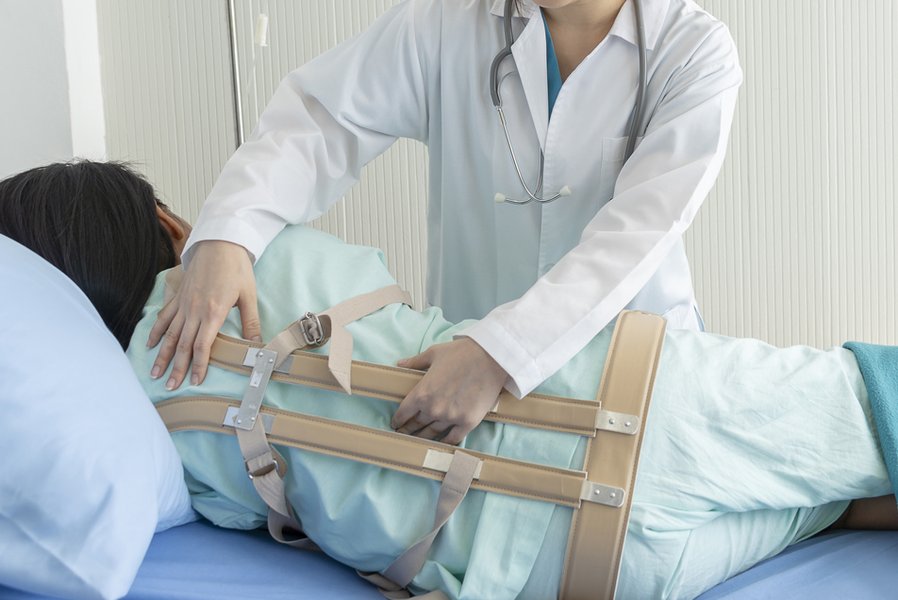
Spinal immobilization devices, while necessary for healing, contribute to prolonged inactivity that affects mineral balance.
Factors Influencing Phosphorus Dynamics
The extent of hyperphosphatemia can vary depending on several factors:
- Duration and Severity of Immobilization: Longer periods and more complete inactivity generally lead to more pronounced effects.
- Baseline Bone Health: Individuals with higher bone turnover rates (e.g., adolescents) might experience more significant changes.
- Underlying Renal Function: Pre-existing kidney issues can impair phosphorus excretion further, worsening hyperphosphatemia.
- Hormonal Status: The degree of PTH suppression plays a key role.
- Nutritional Intake: While dietary phosphorus intake isn't the primary cause, excessive intake could potentially add to the burden. Phosphate supplementation, however, has shown mixed results in studies.
- Medical Interventions: Treatments like bisphosphonates, which inhibit bone resorption, can help manage and normalize phosphorus levels.
Visualizing the Factors Contributing to Hyperphosphatemia Severity
The severity of hyperphosphatemia during chronic immobilization depends on a combination of factors. This radar chart provides a conceptual visualization of the relative importance or potential impact of key contributing elements. The scale represents the potential influence, ranging from lower (closer to the center) to higher (towards the edge), based on general physiological principles.
As visualized, factors like the duration of immobility and underlying kidney health often have a significant impact, while others like baseline bone turnover contribute variably. Understanding these interacting factors helps in assessing individual risk.
Mapping the Process: Immobilization and Phosphorus
This mindmap illustrates the interconnected pathways leading from chronic immobilization to altered phosphorus levels and potential consequences.
The mindmap highlights the two main pathways – increased bone resorption and decreased renal excretion – converging to cause hyperphosphatemia, which in turn can lead to several associated health concerns.
Summary of Key Factors
This table summarizes the primary factors involved in altering phosphorus levels during chronic immobilization and their mechanisms:
| Factor | Effect on Serum Phosphorus | Key Mechanism |
|---|---|---|
| Reduced Mechanical Stress | Indirectly Increases | Triggers imbalance in bone remodeling favoring resorption over formation. |
| Increased Bone Resorption | Directly Increases | Accelerated breakdown of bone matrix releases stored phosphorus into the bloodstream. |
| PTH Downregulation/Altered Effect | Increases | Reduces the signal for kidneys to excrete phosphorus. |
| Decreased Renal Phosphorus Excretion | Directly Increases | Kidneys retain more phosphorus due to increased renal threshold, leading to accumulation in blood. |
Managing Phosphorus Levels
While hyperphosphatemia can occur during immobilization, understanding its causes helps in management. Monitoring phosphorus levels through blood tests is important for individuals undergoing prolonged immobilization. Management strategies may involve dietary adjustments (though diet is not the primary cause here) and sometimes medications like bisphosphonates that specifically target and reduce bone resorption, thereby lowering the release of phosphorus and calcium from bones.
This video discusses phosphorus management, primarily in the context of kidney disease, but offers insights into dietary awareness and binders which can be relevant for managing high phosphorus levels from various causes.
Frequently Asked Questions (FAQ)
Why does lack of movement cause bone to release phosphorus?
Bone constantly remodels itself based on mechanical demands. Weight-bearing activity signals bone-building cells (osteoblasts) to strengthen bone. Without these signals during immobilization, bone-resorbing cells (osteoclasts) become relatively more active. They break down bone tissue to release minerals like calcium (partly to maintain blood calcium levels) and phosphorus (which is structurally linked to calcium in bone), leading to mineral release into the bloodstream.
Is the hyperphosphatemia from immobilization dangerous?
Mild to moderate hyperphosphatemia might not cause immediate symptoms, but chronic elevation can be problematic. It contributes to bone density loss (osteoporosis) and, especially when combined with high calcium levels, increases the risk of calcium phosphate depositing in soft tissues like blood vessels (vascular calcification) or kidneys (nephrocalcinosis or stones). The severity of risk depends on the level of elevation, duration, and individual factors like kidney function.
How is immobilization-induced hyperphosphatemia treated?
The primary approach is to address the underlying cause – immobilization – whenever possible through rehabilitation and remobilization. If phosphorus levels are significantly high or persistent, specific treatments may be used. Bisphosphonates (medications like pamidronate or zoledronate) are often effective as they directly inhibit osteoclast activity, reducing bone resorption and thus lowering the release of both phosphorus and calcium. Monitoring fluid intake and kidney function is also important.
Does everyone who is immobilized develop high phosphorus levels?
While the tendency towards increased bone resorption and altered renal handling exists in most immobilized individuals, the degree to which serum phosphorus levels rise can vary. Factors like the duration and completeness of immobilization, age (younger individuals with higher bone turnover may be more affected), baseline kidney function, and individual hormonal responses all play a role. Therefore, not everyone will develop clinically significant hyperphosphatemia, but the risk is elevated.
Is this related to "phosphorus immobilization" in soil?
No, these are opposite concepts using similar terms. In human physiology, "immobilization" refers to the lack of physical movement, which mobilizes phosphorus from bone stores into the blood. In environmental science (e.g., soil or water treatment), "phosphorus immobilization" refers to processes that bind or trap phosphorus, making it less mobile and bioavailable, often to prevent pollution like eutrophication.
Recommended Reading
- Explore the specific effects of prolonged bed rest on bone density.
- Learn more about how Parathyroid Hormone (PTH) regulates calcium and phosphorus balance.
- Discover the common causes and consequences of high phosphorus levels (hyperphosphatemia).
- Investigate how bisphosphonate therapy is used to manage disorders of bone metabolism.
References
Last updated May 4, 2025