
Unraveling the Intersections: MCAS, POTS, and Ankylosing Spondylitis
Exploring the potential links between mast cell activation, postural tachycardia, and inflammatory arthritis.
While seemingly distinct, Mast Cell Activation Syndrome (MCAS), Postural Orthostatic Tachycardia Syndrome (POTS), and Morbus Bechterew (more commonly known as Ankylosing Spondylitis or AS) may share underlying connections rooted in the body's immune and autonomic nervous systems. Research is increasingly highlighting overlaps and potential shared pathways, particularly concerning inflammation and immune dysregulation.
Key Insights into the Connections
- Immune & Inflammatory Overlap: All three conditions involve aspects of immune system dysregulation and inflammation. AS is a known autoimmune inflammatory condition, MCAS involves inappropriate immune cell (mast cell) activation leading to inflammation, and POTS is increasingly linked to inflammatory and autoimmune processes.
- MCAS-POTS Link: There is a recognized association between MCAS and POTS. Mast cell mediators released during MCAS activation can directly impact blood vessels and autonomic nerve function, potentially triggering or mimicking POTS symptoms like tachycardia upon standing.
- Autonomic Dysfunction Potential: POTS is fundamentally a disorder of the autonomic nervous system. Emerging evidence suggests that autonomic dysfunction can also be present in patients with inflammatory conditions like Ankylosing Spondylitis, providing another potential point of convergence.
Defining the Conditions
To understand the potential links, let's briefly define each condition:
Mast Cell Activation Syndrome (MCAS)
MCAS involves mast cells (a type of immune cell) inappropriately releasing various chemical mediators (like histamine). This can cause a wide array of symptoms across multiple body systems, often mimicking allergic reactions, but also including cardiovascular, neurological, and gastrointestinal issues.
Postural Orthostatic Tachycardia Syndrome (POTS)
POTS is a form of dysautonomia (autonomic nervous system dysfunction). It's characterized by an excessive increase in heart rate (tachycardia) upon assuming an upright posture, without a significant drop in blood pressure. Symptoms often include lightheadedness, fainting, fatigue, brain fog, and palpitations.
Morbus Bechterew (Ankylosing Spondylitis - AS)
AS is a chronic, inflammatory autoimmune disease primarily affecting the axial skeleton, especially the spine and sacroiliac joints. It causes pain, stiffness, and can lead to fusion of the vertebrae over time, limiting mobility. Inflammation can also affect other joints, eyes, and organs.
The Established Link: MCAS and POTS
The connection between MCAS and POTS is increasingly recognized in clinical practice and research. While the exact prevalence varies, a significant portion of POTS patients may also have underlying MCAS.
How are MCAS and POTS Connected?
Mast Cell Mediators and Autonomic Function
The primary proposed link involves the chemical mediators released by activated mast cells in MCAS. Substances like histamine, prostaglandins, and tryptase can:
- Affect Blood Vessels: Cause vasodilation (widening of blood vessels), which can contribute to blood pooling in the lower extremities upon standing – a key issue in POTS.
- Influence Heart Rate: Directly or indirectly impact heart rate and rhythm.
- Impact Nerves: Affect autonomic nerve function, further disrupting the body's ability to regulate heart rate and blood pressure in response to postural changes.
Therefore, the systemic effects of mast cell mediator release in MCAS can directly cause or significantly exacerbate POTS symptoms. Some individuals initially diagnosed with POTS may later be found to have MCAS as the underlying driver or a major contributing factor.
Symptom Overlap
Both conditions can present with a wide range of overlapping symptoms beyond postural tachycardia, including fatigue, brain fog, headaches, gastrointestinal issues (like nausea or altered motility), flushing, and shortness of breath. This overlap can sometimes make differentiating the two conditions challenging without specific testing.
Inflammation and Immune Dysregulation: The Common Thread
A crucial theme connecting MCAS, POTS, and AS is the underlying presence of inflammation and immune system dysregulation.
Ankylosing Spondylitis: The Autoimmune Inflammatory Anchor
AS is fundamentally an autoimmune disease where the immune system mistakenly attacks the body's own tissues, primarily in the spine and joints, leading to chronic inflammation. Key inflammatory pathways involving cytokines like IL-17 and TNF-alpha are central to its pathogenesis.
MCAS: Immune Cells Gone Rogue
MCAS represents a dysfunction within the immune system where mast cells are inappropriately activated, releasing potent inflammatory mediators. While not strictly autoimmune in the same way as AS, it is a disorder of immune regulation leading to inflammatory symptoms.
POTS: An Inflammatory Connection?
While traditionally viewed as a neurological/autonomic disorder, growing evidence links POTS to inflammatory and autoimmune processes. Some studies suggest:
- Elevated inflammatory markers in some POTS patients.
- Potential autoimmune mechanisms involving autoantibodies targeting autonomic receptors.
- Frequent co-occurrence with known autoimmune conditions.
- Association with preceding infections, which can trigger immune responses.
Systemic inflammation, whether from AS, MCAS, or other sources, could potentially contribute to autonomic dysfunction and POTS symptoms.
Visualizing the Potential Interconnections
The relationships between these conditions are complex and multifaceted. This mindmap illustrates the core concepts that potentially link MCAS, POTS, and Ankylosing Spondylitis.
MCAS, POTS, AS"] ["Immune System Dysregulation"] ["MCAS (Mast Cell Activation)"] ["AS (Autoimmunity)"] ["POTS (Possible Autoimmune/Inflammatory Links)"] ["Inflammation"] ["AS (Chronic Joint/Spinal Inflammation)"] ["MCAS (Mediator Release)"] ["POTS (Systemic Inflammation Contribution)"] ["Autonomic Nervous System Dysfunction"] ["POTS (Primary Feature)"] ["MCAS (Mediator Effects on ANS)"] ["AS (Potential Secondary ANS Involvement)"] ["Shared Symptom Clusters"] ["Fatigue"] ["Pain (Joint/Systemic)"] ["Gastrointestinal Issues"] ["Neurological Symptoms (Brain Fog)"] ["Genetic Predisposition"] ["AS (HLA-B27)"] ["MCAS/POTS (Emerging Research)"] ["Possible Overlapping Susceptibilities"] ["Connective Tissue Factors (Indirect Link via EDS/HSD)"] ["POTS & MCAS often co-occur with EDS/HSD"] ["Potential for shared underlying factors"]
Comparing Symptom Profiles and Underlying Mechanisms
This chart provides a comparative overview of the relative prominence of key features across MCAS, POTS, and AS based on current understanding. Note that individual experiences can vary greatly.
As illustrated, AS is dominated by inflammation and joint/spinal issues, POTS by autonomic symptoms and fatigue, and MCAS by mast cell-related symptoms, inflammation, and fatigue. However, significant overlaps exist, particularly in fatigue, GI issues, and neurological complaints, highlighting the potential for interplay between these conditions.
Exploring Autonomic Dysfunction in Inflammatory Disease
While POTS is defined by autonomic dysfunction, there's evidence suggesting that the autonomic nervous system can also be affected in chronic inflammatory conditions like Ankylosing Spondylitis.
Potential Mechanisms
- Inflammatory Mediators: Systemic inflammation and circulating cytokines (common in AS) might directly impact autonomic nerve function or central autonomic control centers.
- Autoantibodies: In some autoimmune conditions, antibodies targeting autonomic structures have been identified, although this is less established in AS compared to other diseases.
- Chronic Pain and Stress: The chronic pain, stress, and reduced mobility associated with AS can also influence autonomic nervous system balance over time.
While not typically presenting with the dramatic postural tachycardia of POTS, individuals with AS might experience more subtle signs of autonomic imbalance, such as altered heart rate variability, digestive issues, or temperature regulation problems. If significant orthostatic intolerance occurs in someone with AS, co-existing POTS or MCAS should be considered.
Summary Table: MCAS vs. POTS vs. AS
This table provides a concise comparison of the key characteristics and potential areas of overlap.
| Feature | MCAS (Mast Cell Activation Syndrome) | POTS (Postural Orthostatic Tachycardia Syndrome) | AS (Ankylosing Spondylitis / M. Bechterew) |
|---|---|---|---|
| Primary System Affected | Immune System (Mast Cells) | Autonomic Nervous System | Immune System (Autoimmune) / Musculoskeletal (Spine/Joints) |
| Core Mechanism | Inappropriate mast cell mediator release | Orthostatic intolerance due to autonomic dysregulation | Autoimmune inflammation targeting entheses, spine, and joints |
| Hallmark Symptom(s) | Multi-systemic allergic-like reactions, flushing, GI upset, pain | Excessive heart rate increase upon standing, lightheadedness, fatigue | Chronic back pain, stiffness (esp. morning), reduced spinal mobility |
| Inflammation Role | Key feature (mediator-driven) | Increasingly implicated; potential inflammatory/autoimmune subtypes | Primary driver (autoimmune) |
| Autonomic Dysfunction Role | Can be triggered by mediators | Defining characteristic | Possible secondary involvement due to inflammation/other factors |
| Potential Connection Points | Shared inflammatory pathways, mediator effects on ANS, symptom overlap (fatigue, GI, neuro) | Shared inflammatory pathways, symptom overlap, possible shared autoimmune links | Shared inflammatory pathways, potential secondary ANS effects, symptom overlap (fatigue, pain) |
Visualizing Ankylosing Spondylitis
Ankylosing Spondylitis primarily impacts the spine and sacroiliac joints. The chronic inflammation can lead to characteristic changes visible on imaging over time, including erosion, sclerosis (hardening of bone), and eventual fusion of vertebrae ("bamboo spine"). Understanding these structural changes helps differentiate AS from conditions like MCAS and POTS, which do not typically cause these specific skeletal alterations.
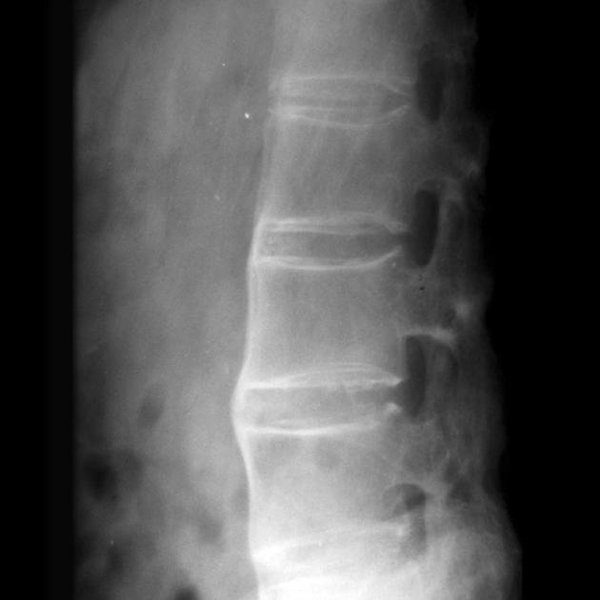

Left: X-ray showing changes in the lumbar spine typical of AS. Right: Imaging highlighting inflammation in the sacroiliac joints.
Understanding Autoimmunity and Mast Cell Roles
This video explores the intersection of autoimmunity, mast cell activation, and dysautonomia, providing valuable context for how these systems can interact and contribute to complex conditions like those discussed.
Dr. Brent Goodman discusses the links between autoimmune processes, mast cell activity, and autonomic dysfunction (dysautonomia), offering insights relevant to understanding potential overlaps between AS (autoimmune), MCAS (mast cell), and POTS (dysautonomia).
Frequently Asked Questions (FAQ)
Can having one of these conditions increase the risk for another?
Yes, there appears to be an increased co-occurrence, particularly between MCAS and POTS. The relationship with AS is less direct but plausible through shared inflammatory or immune pathways. Having AS might not directly cause POTS or MCAS, but the underlying systemic inflammation or potential autoimmune factors could create a susceptibility or contribute to symptoms that overlap or mimic these conditions. Similarly, the chronic inflammation from MCAS could potentially influence autonomic function over time.
Is Morbus Bechterew (AS) part of the EDS/POTS/MCAS "trifecta"?
No, Ankylosing Spondylitis (Morbus Bechterew) is not typically considered part of the commonly referenced "trifecta" or "triad," which usually refers to the frequent co-occurrence of hypermobile Ehlers-Danlos Syndrome (hEDS) or Hypermobility Spectrum Disorder (HSD), POTS, and MCAS. While AS shares features like inflammation and potential immune dysregulation, its primary pathology (autoimmune attack on the spine/joints) and genetic links (like HLA-B27) differ from the typical profile of the EDS/POTS/MCAS cluster, which often involves connective tissue abnormalities.
How are these conditions diagnosed if symptoms overlap?
Diagnosis requires specific criteria for each condition. POTS is often diagnosed via tilt table testing or active stand tests measuring heart rate changes. MCAS diagnosis involves characteristic symptoms plus evidence of mast cell mediator release (e.g., elevated serum tryptase during a symptomatic episode, or elevated urine mediators) and response to mast cell-targeted treatments. AS diagnosis relies on clinical symptoms (inflammatory back pain), imaging (X-ray or MRI showing sacroiliitis or spinal changes), and sometimes genetic testing (HLA-B27), along with inflammatory markers in blood tests. Careful clinical evaluation is needed to differentiate and identify co-existing conditions.
Does treatment for one condition help the others?
Sometimes, yes. Treatments targeting mast cell stabilization or blocking mediators (for MCAS) can potentially improve POTS symptoms if mast cell activation is a contributing factor. Managing systemic inflammation in AS with biologics or other anti-inflammatory drugs might theoretically lessen factors contributing to autonomic symptoms or general malaise that overlaps with POTS/MCAS, but they don't directly treat POTS or MCAS core mechanisms. POTS treatments (like hydration, salt, compression, exercise, and sometimes medication) focus on managing orthostatic intolerance and might not significantly impact AS or MCAS unless symptoms were exacerbated by poor circulation or deconditioning. A comprehensive approach addressing all diagnosed conditions is usually necessary.
References
-
Mast Cell Activation Syndrome – An Overview - PoTS UK
- A Tale of Two Syndromes – POTS and MCAS - Dysautonomia International
-
Ankylosing Spondylitis: From Cells to Genes - PMC - NCBI
- Mast Cell Activation Disorder and Postural Orthostatic Tachycardia Syndrome: A Clinical Review - AHA Journals
- POTS and MCAS: What is the link? - The EDS Clinic
- Comorbidities - Mast Cell Action
- Mast Cell Activation Syndrome, Postural Orthostatic Tachycardia Syndrome, and Ehlers-Danlos Syndrome: What Is The Connection? - Dr. Becky Campbell
Recommended Reading
Last updated April 5, 2025