
Understanding Hyperuricemia: Causes, Symptoms, and Management
Unraveling the complexities of high uric acid levels and their impact on your health.
Hyperuricemia is a medical condition characterized by abnormally high levels of uric acid in the blood. Uric acid is a natural waste product formed when the body breaks down purines, substances found in certain foods and naturally produced by the body. Normally, uric acid dissolves in the blood, passes through the kidneys, and is excreted in urine. However, when there's an imbalance—either too much uric acid is produced, or not enough is eliminated—it accumulates, leading to hyperuricemia. While often asymptomatic, prolonged hyperuricemia can lead to serious health complications like gout and kidney stones.
Key Insights into Hyperuricemia
- Silent Threat: Hyperuricemia often presents without noticeable symptoms, making routine blood tests crucial for early detection, especially if risk factors are present.
- Gout and Kidney Stones: The most common and painful consequences of hyperuricemia are gout, a type of inflammatory arthritis caused by uric acid crystal deposition in joints, and kidney stones, which form from concentrated uric acid in the kidneys.
- Lifestyle and Medication: Management typically involves a combination of lifestyle modifications, such as a low-purine diet, reduced alcohol intake, and increased physical activity, along with medications like xanthine oxidase inhibitors for symptomatic cases.
Delving into Hyperuricemia: Definition and Pathophysiology
Hyperuricemia is fundamentally defined by elevated serum uric acid levels. For women, this is typically greater than 6 mg/dL, and for men, greater than 7 mg/dL. In youth, levels exceeding 5.5 mg/dL are considered hyperuricemia. Uric acid itself is a byproduct of purine metabolism. Purines are nitrogen-containing compounds essential for DNA and RNA synthesis, and they are abundant in certain foods like red meat, organ meats, and some seafood. When purines are broken down, they produce xanthine, which is then converted to uric acid by an enzyme called xanthine oxidase. This uric acid is then primarily excreted by the kidneys.
The pathophysiology of hyperuricemia involves an imbalance in this delicate process. There are two main mechanisms leading to high uric acid levels:
Increased Uric Acid Production
This can occur due to a diet rich in purines, excessive alcohol consumption (especially beer and spirits), or high intake of fructose, which can stimulate uric acid production. Certain medical conditions, like rapid cell turnover seen in some cancers or during chemotherapy, can also significantly increase purine breakdown and, consequently, uric acid levels.
Decreased Uric Acid Excretion
This is the more common cause of hyperuricemia. The kidneys play a vital role in filtering and excreting uric acid. Impaired kidney function, whether due to chronic kidney disease, dehydration, or certain medications (such as diuretics), can lead to insufficient uric acid elimination. Conditions like acidosis (e.g., diabetic ketoacidosis) can also lead to organic acids competing with urate for tubular secretion, further reducing excretion.
An illustration depicting the various factors contributing to hyperuricemia.
Common Symptoms and Associated Conditions
A significant aspect of hyperuricemia is its often asymptomatic nature. Many individuals have elevated uric acid levels without experiencing any immediate symptoms. This is why it is often detected during routine blood tests or when complications arise. When symptoms do occur, they are typically related to the complications of hyperuricemia, primarily gout and kidney stones.
Gout: The Painful Arthritis
Gout is the most well-known consequence of hyperuricemia. When uric acid levels remain high for an extended period, uric acid crystals (monosodium urate) can form and deposit in joints, tendons, and surrounding tissues. This deposition triggers a powerful inflammatory response, leading to acute gouty arthritis attacks. Common symptoms include:
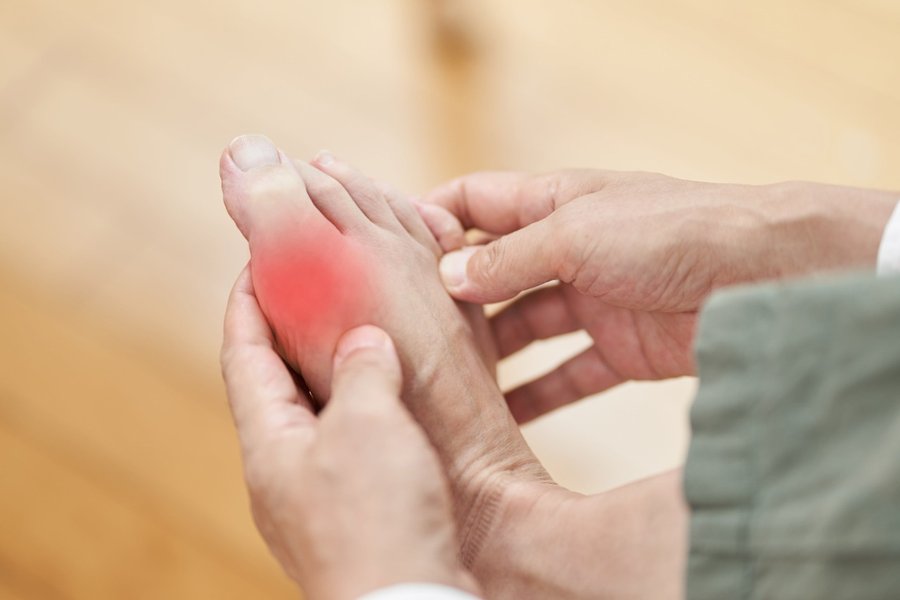
- Sudden, Severe Pain: Often affecting a single joint, most commonly the big toe (podagra), but also seen in ankles, knees, wrists, and elbows. The pain can be excruciating and comes on suddenly, often at night.
- Swelling and Redness: The affected joint becomes hot, swollen, and tender to the touch.
- Tophi: In chronic cases, prolonged hyperuricemia can lead to the formation of tophi, which are visible, hard lumps of uric acid crystals under the skin, around joints, or in the earlobes. These can cause joint damage and disfigurement.
Kidney Stones: Renal Complications
Uric acid can also crystallize in the urinary tract, leading to the formation of uric acid kidney stones. These stones can cause severe pain and other urinary symptoms:
- Severe Pain: Sharp, intense pain in the back or side, often radiating to the groin.
- Blood in Urine (Hematuria): Uric acid stones can irritate the urinary tract, leading to visible or microscopic blood in the urine.
- Frequent and Painful Urination: Stones can obstruct urine flow, leading to increased urgency and discomfort during urination.
- Nausea and Vomiting: Often accompanying severe pain.
Beyond gout and kidney stones, persistent hyperuricemia has been associated with other health conditions, including hypertension, cardiovascular disease, metabolic syndrome, and chronic kidney disease, although a definitive causal link is still a subject of ongoing research.

Microscopic view of uric acid crystals, the culprits behind gout and certain kidney stones.
Diagnostic Approaches
Diagnosing hyperuricemia primarily involves blood tests to measure serum uric acid levels. Given that many people with hyperuricemia are asymptomatic, these tests are often performed as part of a routine check-up or when a patient presents with symptoms suggestive of gout or kidney stones. If gout is suspected, a doctor might also perform a joint fluid aspiration to examine the fluid under a microscope for the presence of uric acid crystals, which provides a definitive diagnosis of gout.
Here's a breakdown of diagnostic considerations:
- Blood Tests: The most common method to measure uric acid levels. Repeated measurements may be necessary to confirm persistent elevation.
- Urine Tests: A 24-hour urine collection can help determine if the hyperuricemia is due to overproduction or underexcretion of uric acid, guiding treatment strategies.
- Joint Fluid Analysis: For suspected gout, fluid from an affected joint is drawn and examined for uric acid crystals.
- Imaging Tests: X-rays, ultrasound, or CT scans may be used to identify kidney stones or evaluate joint damage in chronic gout.
Management and Treatment Strategies
The approach to treating hyperuricemia depends on whether the patient is experiencing symptoms and the severity of the condition. Asymptomatic hyperuricemia often doesn't require pharmacologic treatment, but lifestyle modifications are generally recommended.
Lifestyle Modifications: First Line of Defense
For individuals with hyperuricemia, especially those who are asymptomatic or have mild symptoms, lifestyle changes are crucial. These include:
- Dietary Changes: Limiting purine-rich foods (e.g., red meat, organ meats, shellfish), reducing high-fructose corn syrup beverages and foods, and avoiding excessive alcohol consumption.
- Hydration: Increasing water intake can help the kidneys excrete uric acid more efficiently and prevent kidney stone formation.
- Weight Management: Achieving and maintaining a healthy weight can significantly lower uric acid levels.
- Exercise: Regular physical activity can contribute to overall health and help manage uric acid levels.
Pharmacological Interventions: When Medications Are Needed
When lifestyle changes are insufficient or if the patient experiences recurrent gout attacks, kidney stones, or other complications, medication may be prescribed. The goals of pharmacotherapy are to lower uric acid levels and prevent crystal formation. Key medication categories include:
- Xanthine Oxidase Inhibitors (XOIs): These are the mainstay of treatment for chronic hyperuricemia. They work by blocking the enzyme xanthine oxidase, thereby reducing the production of uric acid. Common examples include allopurinol and febuxostat. Allopurinol is generally the preferred first-line agent.
- Uricosuric Agents: These medications, such as probenecid, help the kidneys excrete more uric acid through urine. They are often used when XOIs are not effective or contraindicated.
- Uricase Enzymes: Drugs like rasburicase and pegloticase convert uric acid into a more soluble substance called allantoin, which is easier for the body to excrete. These are typically reserved for severe, refractory cases or in specific situations like tumor lysis syndrome.
The following table summarizes common approaches to managing hyperuricemia:
| Treatment Type | Mechanism of Action | Primary Use Cases | Examples |
|---|---|---|---|
| Lifestyle Modifications | Reduce purine intake, promote uric acid excretion, improve overall metabolic health | Asymptomatic hyperuricemia, adjunct to medication, prevention | Low-purine diet, hydration, weight loss, exercise, alcohol reduction |
| Xanthine Oxidase Inhibitors (XOIs) | Block uric acid production by inhibiting xanthine oxidase | Chronic hyperuricemia, gout prevention, chemotherapy-related hyperuricemia | Allopurinol, Febuxostat |
| Uricosuric Agents | Increase uric acid excretion by the kidneys | When XOIs are ineffective or contraindicated, patients with underexcretion | Probenecid, Lesinurad |
| Uricase Enzymes | Convert uric acid to more soluble allantoin for excretion | Severe, refractory gout; tumor lysis syndrome | Rasburicase, Pegloticase |
| Acute Gout Treatment | Reduce inflammation and pain during acute attacks | Acute gout flares | NSAIDs, Colchicine, Corticosteroids |
Here's a relevant video providing further insights into gout, a primary consequence of hyperuricemia:
An educational video explaining gout, its causes, pathophysiology, risk factors, and treatment, offering a deeper dive into the most common manifestation of hyperuricemia.
Assessing Treatment Effectiveness and Risk Factors
Monitoring uric acid levels through regular blood tests is essential to assess the effectiveness of treatment and make necessary adjustments. The target uric acid level for most patients with gout is typically below 6 mg/dL, and sometimes even lower, depending on the severity and presence of tophi. Beyond specific levels, the reduction in the frequency and severity of gout flares, or the prevention of new kidney stones, are key indicators of successful management.
Many factors contribute to the risk of developing hyperuricemia, including:
- Genetics: A family history of gout or hyperuricemia increases susceptibility.
- Diet: High intake of purine-rich foods, high-fructose corn syrup, and excessive alcohol.
- Obesity: Higher body mass index is associated with increased uric acid levels.
- Certain Medications: Diuretics (thiazides, loop diuretics) are known to increase uric acid.
- Medical Conditions: Kidney disease, hypertension, metabolic syndrome, insulin resistance, and hypothyroidism.
- Age and Gender: More common in men, and incidence increases with age.
The following radar chart illustrates the relative impact of various factors on the risk of developing symptomatic hyperuricemia and its complications. The closer a point is to the outer edge, the higher its perceived influence on the risk.
Frequently Asked Questions About Hyperuricemia
What exactly is uric acid?
Is hyperuricemia always symptomatic?
What are the primary health risks associated with hyperuricemia?
Can diet alone manage hyperuricemia?
How is hyperuricemia treated with medication?
When should I see a doctor for high uric acid?
Conclusion
Hyperuricemia, or elevated uric acid levels in the blood, is a common condition that, while often asymptomatic, can lead to significant health issues such as gout and kidney stones. Understanding its causes—ranging from dietary factors and alcohol consumption to genetic predispositions and kidney dysfunction—is crucial for effective management. While lifestyle modifications form the cornerstone of prevention and early management, pharmacological interventions like xanthine oxidase inhibitors and uricosuric agents are vital for individuals with symptomatic hyperuricemia or those at high risk of complications. Regular monitoring of uric acid levels and adherence to a tailored treatment plan are essential for preventing painful attacks and long-term health consequences, allowing individuals to maintain a better quality of life.
Recommended Further Reading
- How to prevent gout attacks naturally?
- What is the role of purine-rich foods in hyperuricemia?
- What are the different medications used for lowering uric acid levels?
- Explore the connection between hyperuricemia and chronic kidney disease.